
by PSS Admin | Oct 7, 2026 | Gynecomastia
Most men researching gynecomastia surgery want to know one thing first: how big are the incisions, and how visible will the scars be? The short answer is that the majority of modern male breast reduction surgery is minimally invasive, but the full picture depends on your anatomy.
Key Takeaways
- Most gynecomastia surgery today uses minimally invasive techniques with small incisions (often only 3–5 mm), liposuction, and limited gland excision to create a more masculine chest contour.
- How minimally invasive the procedure is depends on whether enlargement comes from excess fat, dense glandular tissue, excess skin, or a combination of all three.
- About 70–80% of male gynecomastia cases can be corrected through tiny, hidden incisions with minimal scarring and relatively fast recovery.
- More advanced cases with significant excess skin may require larger incisions, but the goal remains the least visible scarring possible and a natural appearance.
- A free virtual or in-office gynecomastia consultation with Dr. Miguel Delgado in San Francisco or Marin County can determine which technique fits your anatomy and goals.
Is Gynecomastia Surgery Really Minimally Invasive?
Male breast reduction surgery today is usually minimally invasive, especially when enlargement is mainly fat or moderate glandular tissue without major skin laxity. Modern plastic surgery techniques—micro-cannula liposuction, small areolar incisions, and pull-through gland excision—allow correction of enlarged male breasts through incisions that are often only 3–5 mm long.
"Minimally invasive" still means surgery. It involves anesthesia, tiny incisions, and tissue removal, but with far less trauma to surrounding tissues compared with older open surgical techniques.
Minimally invasive gynecomastia surgery often uses liposuction or energy-assisted techniques to reduce tissue while favoring smaller scars and minimal tissue disruption. Gynecomastia surgery typically combines liposuction with gland excision. Dr. Miguel Delgado focuses on sculpting a natural, masculine chest contour with minimal scarring through outpatient gynecomastia surgery in San Francisco and a relatively short recovery time.
The true level of invasiveness depends on whether you have mostly fat, mostly breast tissue, significant excess skin, or a mix of all three.
Understanding Male Gynecomastia vs. Excess Fat
Gynecomastia is a condition characterized by overdevelopment of true breast gland tissue in males, caused by hormonal imbalances—specifically excess estrogen or low testosterone. It differs from pseudogynecomastia, which is chest fullness caused mostly by excess fat without significant firm gland behind the areola.
Gynecomastia can occur during puberty in adolescent males, and certain medications can contribute to its development. Weight gain and weight fluctuations also influence occurrence. For surgical planning, the underlying cause matters less than what's in the chest area right now: how much is fat versus firm gland, how tight or loose the skin is, and whether the nipple and areola are stretched or sagging.
Accurate diagnosis and classification—from mild Grade 1 through severe Grade 3–4—help set realistic expectations about scars, downtime, and final chest shape. A consultation includes discussing concerns and treatment options and helps determine the best surgical approach for each patient. Candidates should have realistic expectations about surgery results from the start.
Minimally Invasive Options for Fat-Dominant Gynecomastia
When male breasts are mostly fat (pseudogynecomastia), the least invasive option is liposuction-based male breast reduction surgery through two to four tiny incisions. Liposuction can effectively treat pseudogynecomastia with only small incisions, and minimally invasive techniques are best suited for these mild-to-moderate cases.
Several liposuction methods work well for chest contouring:
- Tumescent liposuction uses small incisions for fat removal with fluid infiltration to minimize bleeding
- Power-assisted liposuction reduces bruising and recovery time through vibrating cannula technology
- SmartLipo employs laser energy for fat removal and skin tightening simultaneously
These approaches use 3–4 mm incisions hidden in natural folds or along the areolar border, leading to minimal scarring. In younger patients with good skin elasticity, liposuction alone may be enough to flatten the chest and allow the skin to contract for a firm, masculine appearance naturally.
While lifestyle changes like diet and exercise matter, targeted chest contouring and precise symmetry usually require surgery. Recovery for this group is fast: most patients return to desk work within a few days, wear a compression vest for several weeks, and see swelling largely resolve within four to six weeks.
Minimally Invasive Gland Excision: Pull-Through and Areolar Techniques
True gynecomastia includes firm glandular tissue behind the nipple–areola complex that liposuction alone cannot remove. That is why minimally invasive gland excision is often added to the surgical approach.
The pull-through technique uses a small incision—about 5 mm—at the areolar edge to access and remove excess glandular tissue after liposuction thins and frees the area. Laser ablation can also target glandular tissue with minimal scarring in select cases.
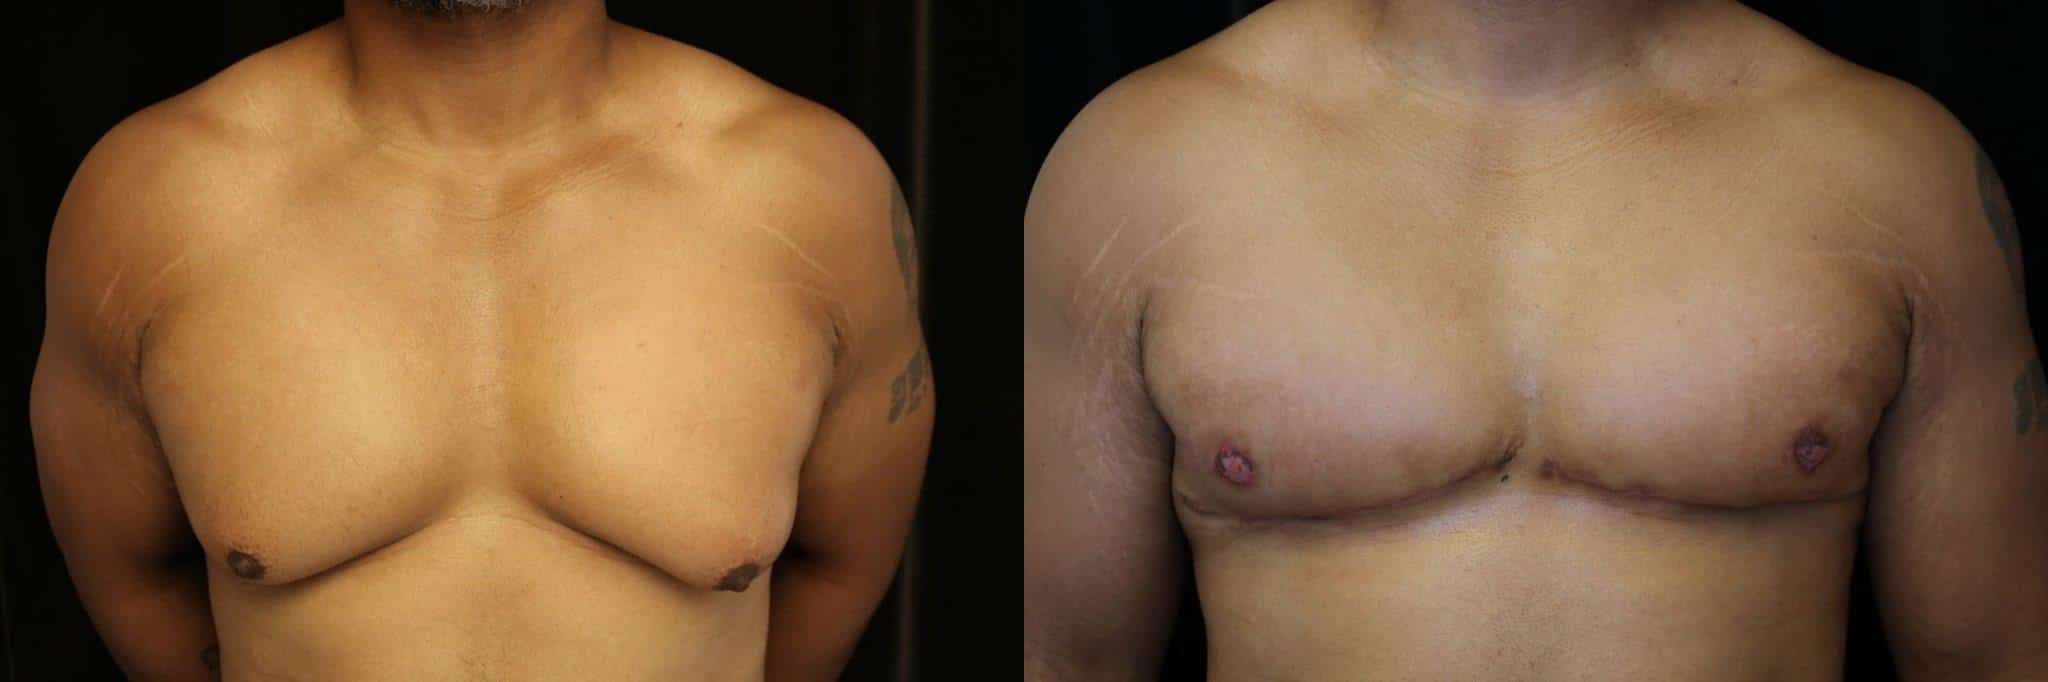
This minimally invasive approach treats many Grade 1 and selected Grade 2 cases, often correcting the problem with only small incisions per side and maintaining well-camouflaged scars. For more moderate cases, Dr. Delgado may use a slightly longer semicircular incision to safely remove dense gland tissue while keeping scars at the areola’s color border. These techniques preserve nipple sensation, maintain natural chest contour in different positions, and avoid crater deformity—the unwanted dishing that results from removing too much tissue directly under the nipple.
When Gynecomastia Surgery Becomes Less Minimally Invasive
Not all men are ideal candidates for tiny-incision approaches. Severe cases of gynecomastia often necessitate traditional excision techniques—particularly when there is significant excess skin from massive weight loss, aging, or sun damage.
Scenarios that require more extensive male breast reduction surgery include:
- Stretched, sagging skin with poor elasticity
- Very low-sitting nipples requiring repositioning
- Skin damaged by stretch marks, photoaging, or genetics
- Large, heavy male breasts classified as Grade III or IV
In these cases, surgical techniques such as periareolar lifts, subcutaneous mastectomy, or double-incision mastectomy with free-nipple grafts create longer scars but allow proper tightening and nipple repositioning. Traditional methods may require larger incisions and longer recovery times compared to minimally invasive techniques.
Even in these less minimally invasive operations, Dr. Delgado places incisions strategically-around the areola or in natural chest folds-to achieve optimal results and minimal visible scarring under clothing. For severe gynecomastia, accepting a larger but well-faded scar is often the only way to gain a flat, masculine chest and remove heavy, uncomfortable, unwanted breast tissue. Patients dealing with excess tissue after significant weight loss may also explore combined body contouring procedures.
What to Expect: Anesthesia, Recovery Time, and Scarring
Most gynecomastia surgeries are performed under general anesthesia or deep sedation in an accredited surgical facility. Surgeons may recommend tests to evaluate health before surgery, and patients may need to stop certain medications beforehand.
Surgery typically takes about 1 to 2 hours. Here's a realistic recovery timeline:
Patients should wear a compression vest during recovery. Swelling and bruising are common in the first few weeks, and pain can be managed with prescribed medication post-surgery. Patients must avoid strenuous activity and return to normal activities gradually. Recovery from minimally invasive gynecomastia surgery is usually faster than from traditional methods.
Scars start pink, flatten over several months, and are often barely visible by 9–12 months. Dr. Delgado's scar-management approach includes silicone therapy, sun protection, and scheduled follow-up visits to support minimal scarring and an effective treatment outcome.
Choosing a Surgeon for Minimally Invasive Male Breast Reduction

Experience in gynecomastia surgery specifically—not just general plastic surgery—matters significantly for achieving a natural, masculine chest with the smallest effective incisions. Plastic surgeons who focus on this procedure and perform it regularly tend to have lower complication rates and higher patient satisfaction.
Dr. Miguel Delgado is a board-certified plastic surgeon specializing in gynecomastia in California, attracting patients from across the San Francisco Bay Area and beyond. During a gynecomastia consultation, he reviews medical history, examines the chest area, classifies the gynecomastia grade, and recommends the least invasive technique that can safely achieve the patient's goals.
Ready to find out which approach is right for you? Schedule a free virtual or in-office consultation with Dr. Delgado in San Francisco or Marin County.

Frequently Asked Questions
Can gynecomastia be treated without surgery?
In teenagers and very young men, hormone-related gynecomastia sometimes improves on its own over one to two years. Weight loss can reduce fat-related fullness but cannot remove true male breast tissue. Once stable, long-standing excess glandular tissue cannot be reliably flattened with non-surgical methods—diet, exercise, creams, supplements—cannot reliably flatten the chest. Surgery remains the only predictable treatment to remove firm glandular tissue and achieve a more masculine chest contour. A consultation helps determine whether observation, lifestyle changes, or surgical male breast reduction is the right next step.
Will minimally invasive gynecomastia surgery leave "scarless" results?
No surgical procedure is truly scarless, but minimally invasive gynecomastia techniques use tiny, discreet incisions that often become very hard to see over time. Incisions placed at the edge of the areola or in natural chest creases heal as thin, flat lines that blend well with surrounding skin. Most patients feel comfortable shirtless after healing and report improved self-confidence and self-esteem, even though a trained eye might find faint scars up close.
How long do results from male breast reduction last?
Removed fat cells and excess breast tissue do not grow back, so results are generally permanent if the patient maintains a stable weight and avoids substances known to trigger gynecomastia. Significant weight gain, anabolic steroids, or certain medications can cause new chest fullness, sometimes described as puffy nipples or returning man boobs. Discuss risk factors with your surgeon before surgery and follow lifestyle recommendations to preserve your flatter chest.
Am I a good candidate for a very minimally invasive technique?
Key factors include mild to moderate breast enlargement, good skin elasticity, stable weight, and no major sagging or very low-positioned nipples. Men with large, heavy male breasts and stretched skin are more likely to need additional skin-tightening incisions for the best result. The only way to know for certain is a hands-on exam where Dr. Delgado can recommend whether liposuction alone, lipo plus pull-through surgical excision, or a more extensive surgical management approach is most appropriate.
Is gynecomastia surgery covered by insurance?
Many insurance plans consider gynecomastia surgery cosmetic and do not cover it, but policies vary. Some may offer partial coverage if specific medical criteria are met, such as documented pain or functional limitations. Check directly with your insurance provider about benefits and documentation requirements. Dr. Delgado's office team can help provide medical records and cost information and can discuss payment options for those paying out of pocket.
by PSS Admin | Aug 26, 2026 | Gynecomastia
Key Takeaways
- Most gynecomastia surgery patients achieve excellent, long-lasting chest contours, but some men may benefit from revision surgery to address residual fullness, contour irregularities, or scarring.
- You should usually wait at least 6–12 months after your first surgery before deciding on revision, so swelling can fully resolve and scar tissue can soften.
- Revision male breast reduction is more complex than initial gynecomastia surgery and should be performed by a board-certified plastic surgeon with extensive revision experience.
- Careful surgeon selection, clear communication during the initial consultation, and strict adherence to aftercare instructions greatly reduce the risk of ever needing another procedure.
- Dr. Miguel Delgado in San Francisco and Marin County is a nationally recognized specialist in primary and revision male breast reduction, offering in-office and virtual consultations with extensive before-and-after photo documentation.
Can a “Botched” or Disappointing Gynecomastia Surgery Be Fixed?
Yes. In most cases, an unsatisfactory initial gynecomastia surgery can be meaningfully improved—and often fully corrected—with properly planned revision male breast reduction surgery performed by a board-certified plastic surgeon with revision experience. For adult men who have already had gynecomastia surgery and now see residual chest fullness, asymmetry, crater deformities, contour irregularities, or visible scars—and for men considering their first procedure who want to understand what revision may involve—knowing what can and cannot be fixed is central to making the right next decision.
Revision gynecomastia surgery corrects these problems and can restore a flatter, more masculine chest, which matters when the first result still affects how your chest looks, how clothes fit, and your confidence. The original operation may have involved liposuction, excision, or both; revision must account for scar tissue, altered anatomy, and limited remaining tissue, which is why choosing the right surgeon matters. Most gynecomastia operations produce good results, yet some patients remain dissatisfied because technical or healing issues affect chest appearance, and revision can often improve both the contour and overall result.
Below, you’ll learn the common reasons men seek revision gynecomastia surgery, the problems revision can address, when it makes sense to wait versus proceed, how candidacy is evaluated, how risk can be reduced, how complex revision surgery differs from a first operation, and why many patients choose Dr. Miguel Delgado for this type of corrective surgery. Every case is unique, so a detailed consultation with a qualified healthcare provider is essential to confirm what can realistically be achieved.
Why Do Some Men Need a Revision After Male Breast Reduction Surgery for Excess Breast Tissue?
Male breast reduction carries very high satisfaction rates. One institutional series reported average cosmetic satisfaction of 9.4 out of 10. Common reasons for revision gynecomastia surgery include:
- Residual glandular tissue or excess fat leaving the chest still looking puffy or feminine, especially when the initial surgery relied on liposuction alone without surgical excision of glandular breast tissue.
- Over-resection causing crater deformity or sunken areas under the areola, the dark skin surrounding the nipple.
- Asymmetry between the two sides in volume, nipple position, or breast size.
- Excess skin or sagging is not fully addressed during the first male breast reduction, particularly in severe cases with significant skin laxity.
- Prominent scars–hypertrophic, widened, or keloid–especially in patients with dark skin surrounding the incision sites.
- Recurrence due to weight gain, hormonal imbalance, certain medications, or use of substances including anabolic steroids.
Some issues are purely technical, while others are biological. Gynecomastia can result in overdeveloped or enlarged breasts in males, and true gynecomastia can occur during puberty because of hormonal imbalances that affect hormone levels; if gynecomastia persists beyond puberty, surgery may be appropriate. Obesity is a contributing factor, as are underlying medical conditions and certain drugs such as anabolic steroids. Excessive alcohol intake and certain prescription medications can also trigger enlarged breast tissue or breast development.
A thorough evaluation is necessary to determine the cause of recurrent gynecomastia and whether gynecomastia may flatten without surgery. Dr. Delgado routinely evaluates outside operative reports and prior photographs to understand exactly what was done during the initial surgery.
Who Is an Ideal Candidate for Revision Gynecomastia Surgery?
Ideal candidates for revision are men who:
- Are at least 18 and have stable, persistent concerns after their first breast reduction surgery, including ongoing physical discomfort or psychological distress.
- Maintain a stable weight and healthy lifestyle for several months before surgery.
- Are willing to quit smoking and stop using nicotine well before and after cosmetic surgery.
- Have addressed contributing causes including hormonal changes, medical conditions, or certain medications with their healthcare provider.
- Hold realistic expectations focused on improving quality of life rather than achieving perfection, and understand the added complexity of revision plastic surgery.
Revision is not appropriate while significant swelling or early scar tissue is still evolving. During the initial consultation, Dr. Delgado performs a detailed physical exam of the chest and pectoral muscles, reviews medical history and prior surgical options, and may recommend laboratory tests if hormone issues are suspected. The preoperative evaluation also considers rare but important causes, such as male breast cancer, and reviews standard surgical risks, like bleeding and infection.
How Long Should I Wait, and Is Revision More Difficult Than the First Surgery?
Revision gynecomastia surgery is usually more technically demanding than the primary operation and should not be rushed. Most plastic surgeons recommend waiting at least six months to one year after surgery before revision because timing is critical. Swelling may take three months or more to resolve fully, and the areola and chest continue to change for many months, so early dissatisfaction often improves on its own.
Several factors make the revision surgical treatment more complex:
- Scar tissue from the first surgery can obscure normal anatomy and make dissection with a thin hollow tube or scalpel more challenging.
- Blood supply to the nipple-areola complex may have changed, requiring a more cautious approach with modified incision patterns.
- Less additional tissue is available, making planning and controlled motion during excision critical.
- Prior liposuction may have removed natural fat layers, raising the risk of contour irregularities if further excess fatty tissue is removed using vacuum suction.
In experienced hands, complication rates remain manageable. Research shows overall complication rates for gynecomastia surgery range from roughly 12% to 22%, with minimally invasive approaches at the lower end. During a consultation, Dr. Delgado provides an honest assessment of what can safely be achieved in a single stage versus situations where staged procedures deliver better results.
How to Reduce the Risk of Ever Needing Revision Gynecomastia Surgery
No operation can guarantee perfection, but thoughtful planning dramatically reduces the chances of needing a second procedure. Here is what you can do:
Before Surgery
- Choose a board-certified plastic surgeon with deep experience in types of gynecomastia and not just occasional cases among other cosmetic procedures; many patients seek out the best gynecomastia surgeon in California to maximize their chances of an excellent outcome.
- Review a large gallery of before-and-after photos of male breasts and enlarged male breasts, including revision cases-look for natural contours and inconspicuous scars.
- Ask how many surgeries the surgeon performs annually and how often they handle revisions from other practices.
- Discuss your goals and what bothers you most so your surgeon can design a precise plan to correct gynecomastia.
- Have a full medical history review covering medications, supplements, and any substance use that may cause enlarged breasts.
After Surgery
- You will need a supportive garment around your chest after surgery. Wear it exactly as advised to reduce swelling and support results.
- Stitches are usually removed one to two weeks after surgery. Avoid heavy exercise for about three weeks post-surgery.
- Recovery may take about a month before you resume normal activities; during the first few weeks, attend all follow-up visits so minor issues can be caught early.
- Maintain a stable weight and avoid substances known to trigger breast tissue growth to protect long-term results.
For a detailed look at what to expect, review this gynecomastia surgery recovery guide.
Why Choose Dr. Miguel Delgado for Revision Gynecomastia Surgery?
Dr. Delgado is a board-certified plastic surgeon in San Francisco and Marin County with a nationally recognized focus on gynecomastia revision and complex male breast reduction surgery. He performs approximately 160 gynecomastia surgeries annually, and roughly 40% of his practice involves revision cases–often from patients who feel self-conscious about results from other surgeons. His training includes UCSF medical school and residencies at Johns Hopkins and Stony Brook.
His practice offers accredited surgical facilities, experienced anesthesia providers, and strict safety protocols. Surgery carries risks in any setting, but an accredited environment with individualized anesthesia planning, whether general anesthesia or another approach, minimizes those risks while addressing even severe pain or emotional discomfort from a previous outcome.
For both local and out-of-town patients, Dr. Delgado provides free virtual or in-office consultations, comprehensive photographic documentation, and personalized recovery plans. Men who want to address gynecomastia, whether it stems from hormonal imbalance, medical conditions, or simply want the self-confidence and self-esteem that come with a chest they feel good about, can explore their treatment and surgical options with a surgeon whose career is built around effective treatment of enlarged male breasts.
If a previous surgery left you unhappy, or you want to minimize the risk of ever needing revision, schedule a consultation and take the next step toward a more confident chest contour.

Frequently Asked Questions About Fixing an Initial Gynecomastia Surgery
Will insurance cover revision male breast reduction surgery?
Most insurers consider gynecomastia surgery and revision male breast reduction to be cosmetic surgery and do not cover them. Rare exceptions exist for cases with documented severe pain or functional impairment.
Can I fix contour irregularities or scars without another full surgery?
Some mild issues may be improved with non-surgical approaches, such as steroid injections into raised scars, microneedling, laser treatments, or limited in-office procedures. However, persistent glandular tissue, significant asymmetry, or excess tissue usually requires formal revision surgery. Dr. Delgado evaluates each case individually and recommends the least invasive effective approach.
How long is the recovery after revision gynecomastia surgery?
Recovery is often similar to the initial procedure. Many men return to desk work within about two weeks, with strenuous exercise restricted for four to six weeks. Because tissues have already been operated on, swelling and firmness can last longer-final results may take 6–12 months to settle fully. Close adherence to compression garment use is essential during the first few weeks.
Is there a limit to how many times gynecomastia surgery can be revised?
There is no fixed numerical limit, but each additional operation increases scar tissue, alters blood supply, and reduces available tissue for surgical removal. This is why choosing a surgeon with extensive revision experience matters. Dr. Delgado will provide an honest assessment of what is safely possible, including whether excessive bleeding or healing concerns affect candidacy.
Can I combine revision gynecomastia surgery with other cosmetic procedures?
In appropriately healthy patients, revision can sometimes be combined with liposuction of the abdomen or flanks, body contouring, or skin tightening. Safety is the priority: total operative time and anesthesia considerations are weighed carefully. These combination options, along with incision planning and reduction mammaplasty details, are best discussed during a personalized consultation where Dr. Delgado can determine what makes sense for your goals and overall health.
About the Author
Dr. Miguel Delgado is a board-certified plastic surgeon in San Francisco specializing in facial rejuvenation, deep plane facelifts, body contouring, and advanced gynecomastia correction — a procedure that reduces male breast size, which certain medications, anabolic steroids, or other drugs can influence. Certified by the American Board of Plastic Surgery, he brings decades of specialized surgical expertise and artistic precision to his practice. Through his blog and patient education resources, Dr. Delgado shares expert insights and guidance to help patients make confident, informed decisions about their aesthetic journey.
Schedule Your Gynecomastia Revision Surgery Today
If you’re ready to fix your previous gynecomastia surgery results, schedule your consultation with Dr. Delgado by calling (415) 898-4161 or fill out our online contact form.
by PSS Admin | Jun 5, 2026 | Gynecomastia Surgery
If you are preparing for gynecomastia surgery or researching what to expect after the procedure, you may wonder why drains are sometimes used. This article explains the purpose of surgical drains, when and why they are needed, what the experience is like, and how they impact your recovery. Understanding this aspect of aftercare can help you feel more confident and prepared for your surgery.
Key Takeaways
Many men are surprised to learn they may require drains after gynecomastia surgery. Dr. Miguel Delgado uses them selectively to improve safety, reduce swelling, and protect chest contour.
- A surgical drain helps remove blood, lymph, and excess fluid from the surgical site.
- Male breast reduction surgery is an effective solution for gynecomastia, and drains are part of post-operative management to optimize recovery by reducing the risk of seroma, hematoma, infection, delayed healing, and contour problems.
- Not every patient needs a drain; the decision depends on the severity of gynecomastia, tissue volume, whether liposuction is performed, and the surgeon’s preference.
- Drains are temporary and typically removed 2 to 5 days after surgery, or once daily drainage falls below 25 to 30 cc.
- Alternatives such as quilting or mattress sutures can help close dead space, but preventing seroma remains the priority.
Understanding Gynecomastia and Male Breast Reduction
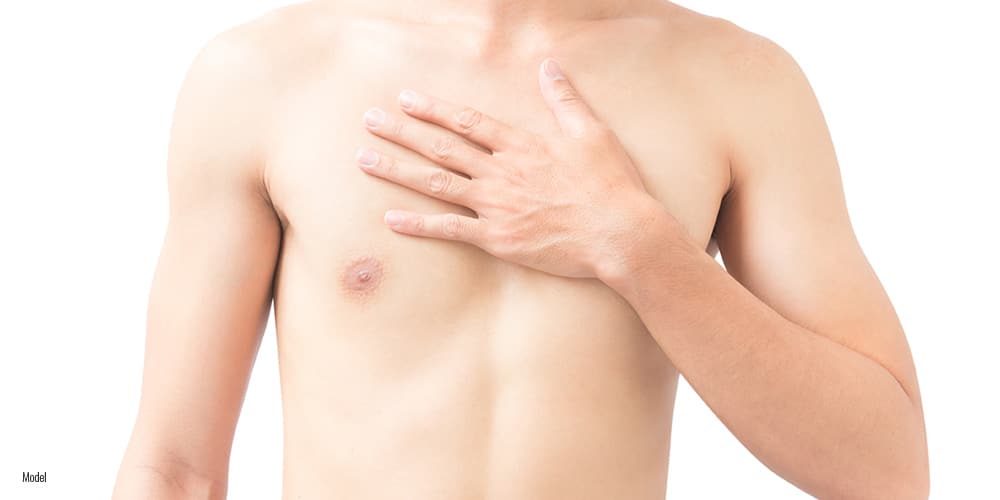
Gynecomastia is the enlargement of male breast tissue and fat. It can occur in teenagers and adults due to puberty-related hormone shifts, aging, medications, anabolic steroids, marijuana or alcohol use, and more. A detailed overview of gynecomastia diagnosis, treatment options, and causes can further clarify how the condition is evaluated and managed.
Symptoms may include puffy nipples, visible breast fullness, tenderness, embarrassment in fitted shirts, and loss of confidence. Male breast reduction surgery is considered the definitive solution for gynecomastia, as it removes breast tissue and fat—often using liposuction plus direct excision through small incisions—to create a flatter chest. Gynecomastia surgery is typically performed as an outpatient procedure, with patients sent home the same day.
The procedure also creates an internal space under the skin where fluid can accumulate.
What Are Post-Operative Drains in Gynecomastia Surgery?
Post-operative drains are tubes used by surgeons to collect excess fluid or blood from the surgical site, preventing accumulation under the skin that can lead to complications such as seromas or hematomas.
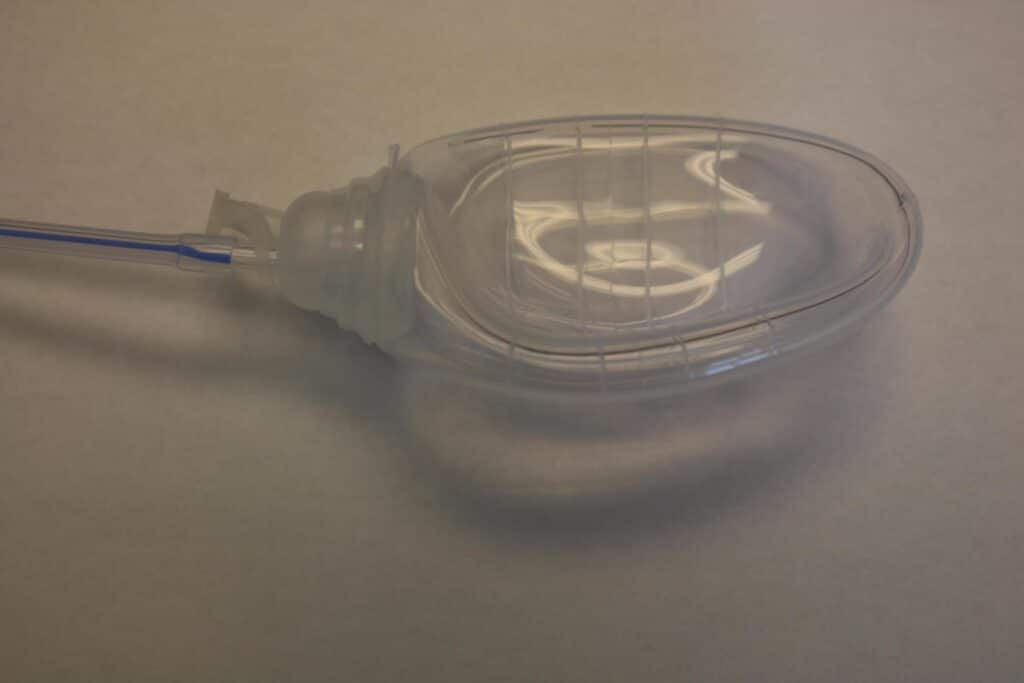
A Jackson-Pratt (JP) drain system is commonly used in surgical procedures. It consists of a thin, flexible silicone tube connected to a drain bulb that provides continuous vacuum suction to draw fluid from the chest cavity. The patient or caregiver squeezes the bulb, caps it, and gentle suction draws fluid into the bulb.
The tube exits through a tiny drain site near the lower chest, a natural crease, or hair-bearing area in the axilla. Drains are common in plastic surgery procedures where large tissue planes are lifted, such as abdominoplasty, breast reduction, and many cases of gynecomastia.
Why Drains Are Often Needed After Gynecomastia Surgery
Gynecomastia surgery leaves an open cavity between the skin and the chest wall. Drains are typically placed in the chest to remove blood and lymphatic fluid that accumulates after the procedure, and are usually left in place for 1 to several days, depending on the volume of drainage.
Drains help:
- remove blood and lymph
- reduce pressure on incisions
- help skin adhere to surrounding tissues
- protect chest shape
- prevent complications during the early healing process
In moderate or severe gynecomastia, more glandular and fatty tissue is removed, creating a larger raw tissue surface. When liposuction is combined with excision, early oozing can be higher. The surgeon’s preference determines the decision to place drains—including the exact location and number—based on the specific procedure and individual patient needs. Dr. Delgado decides whether patients require drains during consultation and may adjust that plan during surgery.
The Design Difference: Channels vs. Perforations
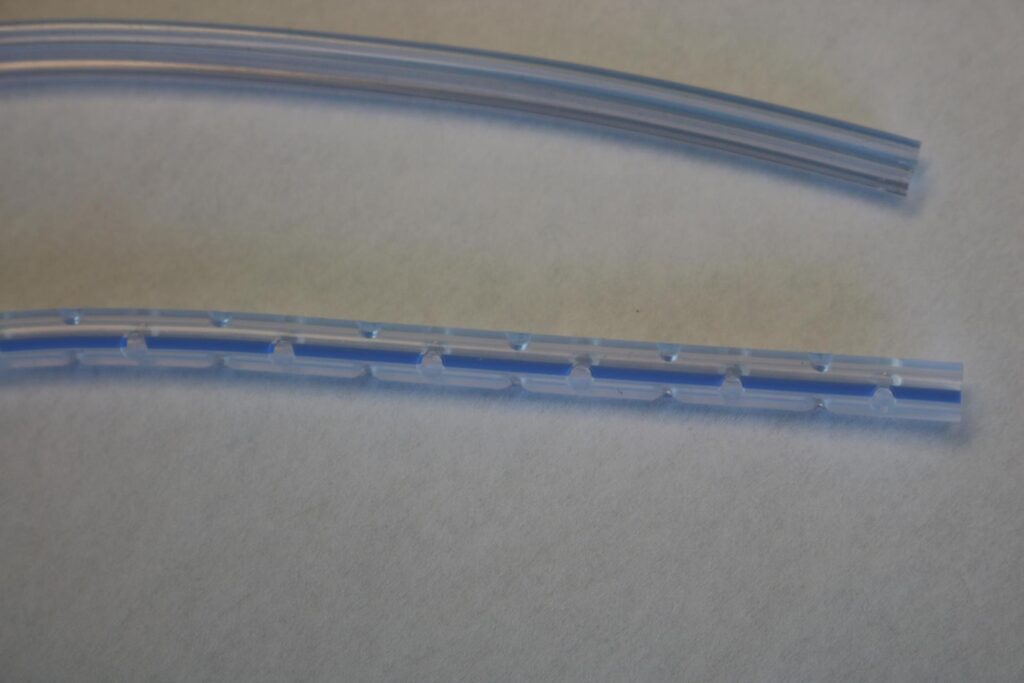
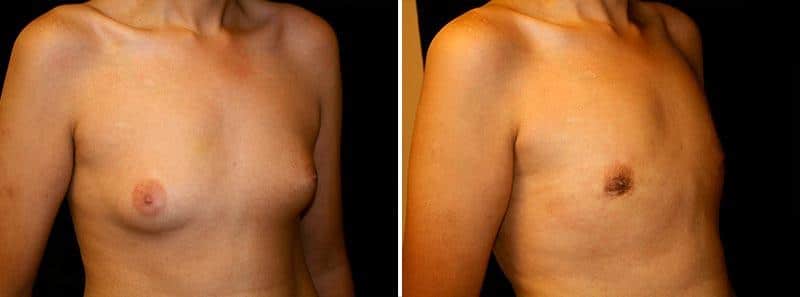
To understand why a channel drain (such as a Blake or Jackson-Pratt channel drain) is significantly more comfortable to remove than a traditional perforated (round) drain, it helps to look at how each type of drain is physically constructed.
Perforated Drains
Traditional perforated drains consist of a hollow, round silicone or rubber tube with several individual holes (perforations) punched into the sides near the tip.
- The Healing Problem: As the body heals, healing tissue (granulation tissue) and small blood clots often grow into these holes.
- The Removal Pain: When the surgeon pulls the drain out, that newly formed tissue has to be forcefully sheared or torn away from the holes. This mechanical ripping of tissue inside the wound bed is the primary cause of the sharp, stinging pain patients feel during removal.
Channel Drains
Instead of a hollow tube with holes, a channel drain features a solid core with four smooth, continuous grooves or channels running along its length. Capillary action draws fluid into these channels, which is then pulled out by suction.
- The Healing Advantage: Because there are no enclosed holes, there are no structural apertures for tissue to grow into and become trapped. Tissue simply rests against the flat, smooth ridges of the outer channels.
- The Removal Comfort: When it is time for removal, the drain glides smoothly over the tissue planes with minimal friction and no tearing, transforming a painful extraction into a sensation that most patients describe as a mild, brief pressure or “slipping” feeling.
Additional Recovery Benefits of Channel Drains
Beyond minimizing pain during removal, the open-groove architecture offers a few other distinct clinical advantages:
- Reduced Secondary Trauma: Because the drain doesn’t tear tissue as it’s removed, there is far less microbleeding in the surgical cavity, lowering the risk of a late-stage hematoma.
- Lower Risk of Clogging (Occlusion): Traditional holes can easily become blocked by a single tissue fragment or blood clot, causing fluid to back up. Channel drains maintain fluid flow through multiple open pathways.
- Kink Resistance: The solid-core design allows the drain to bend and conform to the body’s internal contours without collapsing or kinking, ensuring consistent suction throughout your early recovery.
Seromas, Hematomas, and Other Problems When Drains Are Not Used
Without drains, there is an increased risk of seroma formation, which can lead to discomfort, swelling, and potential infection requiring further medical intervention. A seroma is a pocket of clear yellow fluid that may appear days or weeks after surgery.
The absence of drains can lead to hematoma development, which involves blood pooling in the surgical area, increasing the risk of pain and potentially severe health issues like tissue necrosis. Hematomas usually occur within 24 to 48 hours and may cause sudden swelling, bruising, and a painful, tight chest.
Not using drains can increase the risk of infection, as fluid accumulation creates an ideal environment for bacterial growth, potentially leading to more severe infections. Fluid accumulation without drains can delay healing by physically separating tissues that need to adhere, complicating recovery and potentially leading to poorer aesthetic outcomes.
How Drains Work in Practice: What Patients Can Expect
Most patients worry more about drains than they need to. In the operating room, the surgeon places the tube in the cavity, brings it out through the drain site, secures it, and activates suction before the patient wakes up.
During the first 24 to 72 hours, drainage may look bloody, then lighter or straw-colored. Patients with surgical drains must measure and log fluid output 2 to 4 times a day as part of daily maintenance. Monitoring the fluid volume and color from a surgical drain allows surgeons to track healing progress and detect potential issues early.
Keep a bandage or gauze pad over the drain site. A little leakage is normal. Some surgeons allow showering after 24 to 48 hours; others recommend sponge baths until the drain is removed. If cleared to shower, keep the tubes supported so they do not pull.
Contact your surgeon if you experience bright red blood rapidly filling the bulb, sudden stop in drainage with swelling, fever, increasing tenderness, redness, or worsening pain.

When Are Drains Removed After Male Breast Reduction?
Drain removal happens when output is low and stable. Surgical drains are typically removed two to five days post-surgery or when daily drainage falls below 25 to 30 cc. This timeline may differ for younger patients, and parents dealing with teen surgery should understand teenage gynecomastia and how it affects adolescents before deciding on operative treatment.
Removal is done at a post-operative visit. It is quick and may feel like mild stinging or pressure for a few seconds. After the drains are removed, a small dressing is placed, and minor oozing can occur for a day or two.
Initial results from gynecomastia surgery become visible immediately, but it can take three to six months for all residual swelling to resolve.
Alternatives to Drains: Mattress Sutures and Quilting Techniques
Modern plastic surgery also uses drain-sparing methods. Mattress sutures and quilting sutures tack the undersurface of the chest skin to the pectoral fascia, reducing dead space. For men whose main concern is prominent areolae, especially puffy nipples related to gynecomastia, these techniques can be tailored to improve contour while minimizing fluid buildup.
These sutures can be particularly reassuring for families who have read stories like this mother’s testimony about her son’s gynecomastia journey, showing how careful planning can limit complications and support a smoother emotional experience. These sutures:
- Limit areas where fluid can collect
- Distribute tension
- May reduce post-operative drainage
Quilting sutures reduce the incidence of seroma and hematoma compared to drains alone. In mild cases, compression garments plus sutures may be enough. In larger cases, Dr. Delgado may combine suturing with temporary drains for a safer approach.
The Role of Compression Garments and Overall Aftercare
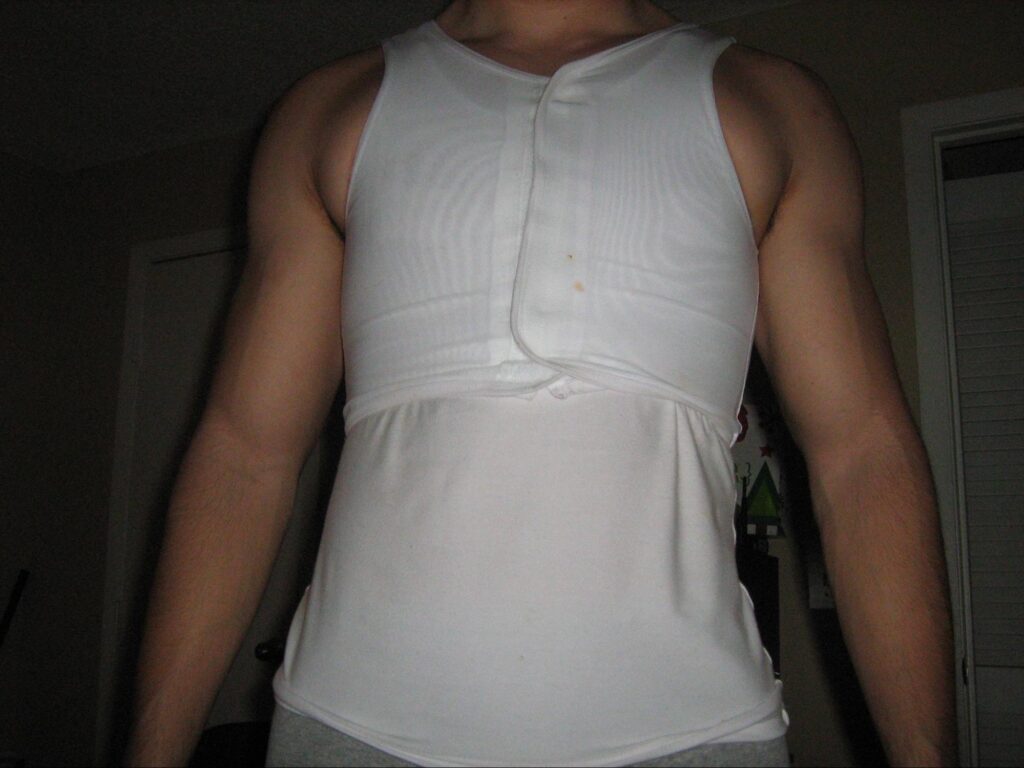
Drains are only one part of recovery. Recovery timelines for gynecomastia surgery may include wearing a supportive compression vest nearly 24/7 for several weeks.
Compression garments help skin settle, reduce swelling, support incisions and the drain site, and promote healing after removal. Seeing how common this condition is—even among well-known celebrities who have dealt with gynecomastia—often encourages patients to stick with their aftercare and focus on long-term results. Patients should avoid heavy lifting and vigorous upper-body workouts for four to six weeks post-surgery to ensure proper healing.
Avoid smoking, nicotine, and unnecessary blood thinners unless prescribed. These precautions support health, reduce bruising, lower the risk of infection, and help patients safely return to normal activities.
Balancing the Benefits and Drawbacks of Drains
Drains are helpful, but they remain foreign objects. They can cause temporary discomfort, pulling, limited arm movement, and the need to record drainage volume. There is also a small risk of infection along the drain tract.
The benefit is that post-operative drains can accelerate healing by preventing fluid buildup, which can create pressure on incisions and disrupt normal healing, ultimately contributing to better aesthetic outcomes.
For many men, several days of drain care are worth it to reduce complications, swelling, scars from revisions, and the risk of a more difficult recovery period.
Dr. Miguel Delgado’s Approach to Drains in Gynecomastia Surgery
Dr. Miguel Delgado is a board-certified plastic surgeon in the San Francisco Bay Area and Marin County with extensive experience in gynecomastia surgery. He evaluates each patient’s breast size, skin quality, medical history, risk factors, and expectations. The use and placement of drains can also depend on the surgeon’s preference and individual surgical technique.
He is more likely to recommend drains for large-volume gland and fat removal, revision surgery, bleeding-risk medications, or combined body contouring procedures. In minimal cases, he may use sutures and compression instead.
If you’re wondering if you need drains after gynecomastia surgery, the best answer is: it depends on your anatomy and risk. Schedule a complimentary virtual or in-office consultation with Dr. Delgado by filling out the online contact form or calling (415) 898-4161 to learn what your procedure is likely to require.
Frequently Asked Questions About Drains After Gynecomastia Surgery
Will having drains increase my risk of infection?
Any foreign object theoretically increases the risk of infection. However, undrained fluid and blood can also feed bacteria. Sterile placement, careful care, and early removal usually make drains protective.
Can I shower and sleep normally with drains in place?
You may be cleared to shower after the drains are removed, and you may need sponge baths at first. Sleep on your back with your upper body elevated, and secure the drain bulb to avoid pulling on the tubes.
Will I need drains for my gynecomastia surgery?
This is decided on a case-by-case basis. Many do not require drains. Dr. Delgado will examine your chest, review photos, and explain whether drains, quilting sutures, compression, or a combined plan is best.
What happens if I develop a seroma even though I had drains?
Seromas can still occur, though drains reduce the risk. Treatment may include office evaluation, needle aspiration, compression, and activity modification until the fluid resolves.
How will I know if something is wrong with my drain?
Call the office the same day for a bulb that will not hold suction, sudden changes in drainage, rapid bleeding, increasing redness, warmth, fever, or worsening tenderness.
by PSS Admin | Jun 4, 2026 | Gynecomastia
Key Takeaways
Current GLP-1 drugs, including semaglutide and tirzepatide, do not directly treat gynecomastia when the problem is true glandular breast tissue. However, they can reduce chest fat in pseudogynecomastia, which may make male breasts look smaller during a weight loss journey.
- GLP-1 medications help with weight loss, blood sugar control, and obesity-related health conditions, but they cannot shrink established glandular breast tissue.
- Persistent male breast enlargement after significant weight loss usually requires male breast reduction surgery for definitive correction.
- A healthcare provider or gynecomastia specialist should distinguish breast tissue from fat using client history, physical exams, clinical features, and when indicated, imaging or hormone levels.
- Dr. Miguel Delgado offers virtual and in-office consultations for men using or considering GLP-1 medications to combat enlarged breasts or planning gynecomastia surgery.
What Are GLP-1 Drugs and How Do They Work?
GLP-1, or glucagon-like peptide-, is a natural hormone released by the gut after eating. It helps regulate blood sugar, appetite, digestion, and fullness.
GLP-1 receptor agonist medications, such as semaglutide, tirzepatide, liraglutide, and newer oral agents, are FDA approved for type 2 diabetes and chronic weight management. Some are taken as a weekly injection, while certain newer agents may be available as a daily pill. Wegovy® contains the active ingredient semaglutide and is used for chronic weight management.
These medications work by helping patients:
- Reduce hunger and food cravings.
- Feel full sooner and longer.
- Slow stomach emptying, which can reduce calorie intake.
Clinical trials show that GLP-1 receptor agonists promote substantial weight loss, often 15-20% in clinical trials, although average weight loss varies by medication, dose, diet, exercise, and starting body weight. GLP-1 therapy is an important tool in obesity care, but these drugs act mainly through appetite and metabolism—not directly changing breast tissue or sex hormone levels.
Gynecomastia vs. Pseudogynecomastia: What’s Really Enlarging the Chest?
“Man boobs” can come from true gynecomastia, pseudogynecomastia, or both. The key difference is whether the enlarged chest is caused by excess glandular tissue, fat accumulation, or a combination of the two.
True gynecomastia is enlarged male breast tissue that feels firm or rubbery under and around the nipple-areola complex. It may affect one or both breasts and is usually driven by a hormonal imbalance. An imbalance between estrogen and testosterone levels can lead to the development of gynecomastia, as estrogen stimulates breast tissue growth while testosterone inhibits it.
Pseudogynecomastia is fatty chest enlargement caused primarily by excess body weight and localized fat. It is more common in men with a higher body mass index or long-standing obesity. Fatty chest tissue often feels soft rather than firm.
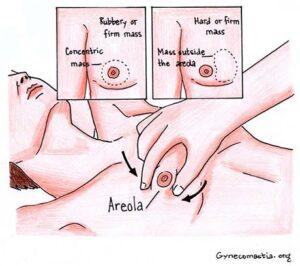
A simple self-check can help: soft, even fullness across the entire body-facing chest area suggests fat, while a firm mound behind the nipple suggests glandular breast tissue. However, a self-exam is not enough. A professional evaluation is important to rule out breast cancer, especially with nipple discharge, a hard one-sided lump, skin changes, or rapidly changing breast size, and to confirm the diagnosis and best treatment options for gynecomastia.
Most adult gynecomastia cases are mixed. That is why weight loss can improve breast enlargement, but may not fully correct enlarged male breast tissue.
Do GLP-1 Drugs Treat Gynecomastia Directly?
The direct answer is no: GLP-1 medications do not remove glandular breast tissue and are not currently considered a direct treatment for gynecomastia. They can, however, reduce the appearance of pseudogynecomastia by helping patients lose fat.
GLP-1 drugs primarily act on:
- Appetite and satiety.
- Blood sugar and insulin response.
- Total body weight and metabolic health.
They do not directly correct the estrogen levels or testosterone levels that cause gynecomastia in many patients. Current data through 2025 show improved body composition and metabolic health, but no strong clinical trials proving that GLP-1 medications reliably reverse established male breast tissue.
Research indicates that GLP-1s can positively influence the male endocrine profile through successful weight reduction. Weight loss via GLP-1 therapy can help improve reproductive health by increasing testosterone levels. Emerging research highlights that medications targeting GLP-1 receptors are effective at treating obesity-related metabolic hypogonadism. By reducing obesity, GLP-1 drugs can help normalize hormone levels.
Still, semaglutide can help reduce body weight and fat, but it does not address the underlying glandular tissue growth associated with gynecomastia, which may necessitate surgical options for complete resolution.
GLP-1 Drugs and Pseudogynecomastia: When Weight Loss Helps the Chest
Pseudogynecomastia responds best to weight loss because the main issue is fat, not true breast tissue growth. For men whose enlarged breasts are mostly fat, GLP-1 therapy can create a visible improvement.
Losing 10-20% of total body weight typically reduces body fat, including fat in the male breast region. GLP-1 drugs can be effective in reducing the appearance of pseudogynecomastia by facilitating significant weight loss. Semaglutide, marketed as Wegovy®, is a GLP-1 drug that aids in weight loss, which indirectly affects gynecomastia by reducing body fat, but does not eliminate the glandular tissue associated with the condition.
Obesity is also a common cause of gynecomastia, as excess fat tissue can convert androgens into estrogens, leading to an increased estrogen-to-testosterone ratio. Adipose tissue contains an enzyme called aromatase, which converts testosterone into estrogen. In simple terms, excess fat can create more estrogen activity in the male chest.
There is one catch: after major fat loss, the remaining firm gland may become more visible. Weight loss achieved through semaglutide can lead to a condition referred to as “Wegovy chest,” which may require surgical intervention for those with persistent gynecomastia after significant weight loss. Men should reassess their chest after weight has been stable for several months.

How Hormones, Health Conditions, and Medications Cause Gynecomastia
Men develop gynecomastia when the estrogen effect outweighs the testosterone effect in male breast tissue. Natural hormone changes can occur in male babies, during puberty, and in men over 50. More than half of adolescent boys may experience temporary breast enlargement during puberty.
Common medical conditions that affect hormone levels and can contribute to teenage gynecomastia during puberty include:
- Primary and secondary hypogonadism, which results in decreased testosterone production, can lead to gynecomastia due to the relative excess of estrogen.
- Chronic kidney disease and liver cirrhosis can cause hormonal imbalances that may lead to gynecomastia.
- Liver disease, liver failure, kidney failure, hyperthyroidism, and obesity-related aromatase activity can increase risk because adipose tissue contains aromatase that converts testosterone into estrogen and converts androgens into estrogens.
- Klinefelter syndrome, pituitary gland problems, adrenal gland disorders, testicular tumors, and some prostate cancer treatments can disrupt testosterone or estrogen balance, including cases of gynecomastia caused by identifiable disorders or syndromes.
Certain medications can also cause gynecomastia. Medications that raise estrogen, lower testosterone, or block androgen receptors can lead patients to develop gynecomastia. This includes some anti-androgens, spironolactone, antidepressants, heart medications, anabolic steroids, alcohol, and marijuana, as well as drugs such as finasteride that have been linked to medication-induced gynecomastia in men.
If you are taking medications and notice tender breasts, swelling, or new breast enlargement, review prescriptions with a healthcare provider. GLP-1 drugs themselves are not currently recognized by major references as common direct causes of gynecomastia, but they can reveal pre-existing breast tissue when fat is lost. Men with hypogonadism or Klinefelter syndrome may also have an increased risk of breast cancer, so evaluation remains important. Not every case can prevent gynecomastia, but early evaluation can identify reversible causes.
When GLP-1 Weight Loss Isn’t Enough: Surgical Male Breast Reduction
When glandular gynecomastia persists after weight loss, gynecomastia surgery is the most definitive gynecomastia treatment. If chronic gynecomastia does not respond to medical treatment, surgical removal of glandular breast tissue is usually required. Surgery is considered the most effective known treatment for gynecomastia, even though targeted exercise and fat loss can help reduce man boobs caused by excess chest fat.
The surgical procedure is customized to the patient. Surgical options for gynecomastia include subcutaneous mastectomy, liposuction-assisted mastectomy, laser-assisted liposuction, and laser-lipolysis without liposuction. Practically, many plastic surgeons combine liposuction for excess fat with direct excision of firm glandular tissue through small incisions near the areola.
After massive weight loss, some men also have excess skin, stretched areolas, or sagging. These patients may need skin removal or more advanced reshaping to restore a masculine chest contour.
Typical recovery includes wearing a compression garment, limiting upper-body exercise for several weeks, and returning to desk work in about one week. Timing matters. Surgery is usually best once body weight is stable, because continued weight changes can affect the result.
Dr. Miguel Delgado’s Approach to Gynecomastia in Men Using GLP-1 Drugs
Dr. Miguel Delgado is a San Francisco Bay Area board-certified plastic surgeon with more than 30 years of experience, specializing in male breast reduction. He has performed thousands of gynecomastia surgeries and routinely evaluates men who have lost significant weight, including patients using GLP-1 medications such as semaglutide or tirzepatide.
40% of Dr.Delgado’s practice is devoted to revision surgery for patients who are unhappy with their prior surgery. This is a testament to his expertise.
His evaluation begins with a detailed history inquiry, including GLP-1 use, weight history, hormone changes, anabolic steroids, medical conditions, and certain medications. He then performs a physical exam to determine whether the issue is fat, glandular breast tissue, loose skin, or a combination of these.
Dr. Delgado customizes treatment for gynecomastia based on anatomy and goals. Some men need targeted liposuction for residual fat. Others need tissue excision, skin tightening, or a more advanced cosmetic procedure after major weight loss.
For men in the San Francisco Bay Area and beyond, Dr. Delgado offers free virtual and in-office consultations to discuss gynecomastia treatment during or after GLP-1 therapy.
Preparing for Gynecomastia Surgery While on GLP-1 Medications
GLP-1 medications slow gastric emptying, which is important for anesthesia safety during elective surgery. Food remaining in the stomach can increase the risk of aspiration.
Many surgeons and anesthesia groups recommend pausing once-weekly GLP-1 injections, such as semaglutide, about 1 to 2 weeks before surgery, and pausing daily oral GLP-1 medications for several days. The exact plan should follow current guidelines and your prescribing clinician’s advice.
Before surgery:
- Patients with diabetes or complex health conditions should coordinate medication changes with their prescribing healthcare provider to avoid blood sugar problems.
- Reach a stable, healthy weight when possible.
- Maintain good protein intake and nutrition.
- Stop smoking or vaping.
- Follow fasting instructions carefully because gastric emptying may be delayed.
Dr. Delgado and his team at Marin Cosmetic Surgery Center provide individualized pre-operative planning for men on GLP-1 medications to support safety, comfort, and aesthetic enhancement.

Psychological Impact and Quality of Life After Male Breast Reduction
Enlarged breasts can cause significant psychological distress, even after successful weight loss. Gynecomastia can lead to low self-esteem, depression, and feelings of shame, and some men find value in acceptance-focused gynecomastia communities and resources.
For many men, treatment is not only about chest shape. It is about mental health, body image, and daily confidence. Men who undergo treatment for gynecomastia typically experience significant improvements in their self-image and confidence, alleviating feelings of embarrassment and self-consciousness.
For example, a man may use Wegovy® to lose substantial weight, then discover that firm breast tissue remains behind the nipple. Surgery can complete the transformation by removing excess breast tissue and improving the masculine chest contour, and it may be reassuring to know that even well-known celebrities have struggled with gynecomastia and sought treatment.
If chest appearance continues to affect your self-esteem despite lifestyle changes or GLP-1 therapy, an expert opinion can clarify your options.
FAQ
Can GLP-1 drugs like semaglutide completely get rid of my gynecomastia?
GLP-1 drugs cannot remove true glandular breast tissue. They mainly reduce fat, so they may improve pseudogynecomastia but rarely eliminate established gynecomastia.
If a firm lump or disc of breast tissue remains after weight loss and hormone-related causes are ruled out, surgery is usually required for complete correction. Schedule an exam with a healthcare provider or gynecomastia surgeon to determine the main cause of your enlarged breasts.
Do GLP-1 medications themselves cause gynecomastia or male breast growth?
As of 2025, major references do not widely recognize GLP-1 agonists as a common direct cause of gynecomastia. What many men notice is the uncovering of pre-existing breast tissue after they lose chest fat, not new breast tissue growth from the drug.
Any new, rapidly growing, painful, or one-sided breast change while on GLP-1 therapy should be evaluated promptly to rule out other conditions.
How can I tell if my enlarged chest is mostly fat or true breast tissue?
Diffuse, soft fullness across the chest suggests fat. A firm, rubbery mound directly under the nipple suggests glandular tissue.
A physician can perform a breast exam, review hormone levels, and sometimes order an ultrasound or mammography. Men who have lost weight on GLP-1 medications and still feel a firm mass behind the nipple may benefit from surgical consultation.
Should I lose weight with GLP-1s before considering gynecomastia surgery?
Reaching or approaching a stable, healthy weight first is usually ideal. It clarifies the proportions of fat and glandular tissue in the chest, thereby improving surgical planning.
GLP-1s can be a powerful tool for appropriate candidates. Results tend to be more predictable once weight has been stable for several months.
Is male breast reduction covered by insurance if I’m on GLP-1 therapy for obesity?
Most insurers consider gynecomastia surgery a cosmetic procedure and deny coverage, regardless of GLP-1 use or weight-loss history, unless strict medical-necessity criteria are met.
Patients should verify benefits directly with their insurance carrier. Dr. Delgado’s practice provides transparent, all-inclusive pricing and can help patients understand financial options for surgery, as well as lifestyle and dietary strategies, such as foods that may influence male breast development.

by PSS Admin | Apr 7, 2026 | Gynecomastia
If you’re someone who takes creatine supplements to support your training, you’ve likely come across alarming claims online suggesting that creatine might cause gynecomastia—the development of enlarged breast tissue in men. These concerns can make any fitness-focused man think twice before mixing their next shake. This guide is for athletes, fitness enthusiasts, and anyone concerned about creatine’s effects on male breast tissue.
In this comprehensive guide, we’ll examine what current research actually says about creatine and gynecomastia, explain why confusion exists, and help you understand when professional evaluation is truly necessary.
Table of Contents
Quick Answer: Does Creatine Cause Gynecomastia?
Based on the latest research, creatine supplementation does not appear to cause gynecomastia in healthy men. This conclusion is supported by decades of clinical trials, systematic reviews, and position statements from organizations such as the International Society of Sports Nutrition.
Gynecomastia is defined as benign enlargement of male breast glandular tissue. It develops when there’s a hormonal imbalance, specifically when estrogen activity outpaces androgen (testosterone) activity at the breast tissue level. Elevated estrogen levels are a key factor in the development of gynecomastia. This is fundamentally different from the muscle growth or water retention associated with creatine use.
No controlled clinical trials or large observational studies have identified creatine as a cause or significant risk factor for gynecomastia. While anecdotal online reports exist, they are not supported by well-designed medical studies. Creatine is one of the most researched sports supplements, with over 1,000 peer-reviewed papers examining its effects—and gynecomastia has not been documented as a side effect in these trials.
Here’s what the evidence tells us:
- No randomized controlled trials report gynecomastia as an adverse event from creatine use.
- Meta-analyses confirm hormonal stability at standard doses of 3–5 g daily.
- Long-term trials spanning up to five years show minimal side effects (primarily transient weight gain from intramuscular water).
- Major sports medicine organizations consider creatine safe for healthy individuals.
At Dr. Miguel Delgado’s gynecomastia-specialty practice in San Francisco and Marin County, we rarely see creatine alone as a true underlying cause of gynecomastia. Most patients presenting with gynecomastia have other identifiable triggers, most commonly anabolic steroid use, certain medications, or obesity-related hormonal changes.

Fit man in a gym holding a water bottle
What Is Creatine?
To understand why creatine is unlikely to cause gynecomastia, it helps to know exactly what this compound does in your body.
Creatine is a naturally occurring compound synthesized from the amino acids arginine, glycine, and methionine. Your liver, kidneys, and pancreas produce roughly 1 g of creatine per day, while an additional 1–2 g typically comes from dietary sources, such as red meat, pork, and seafood. The vast majority—about 95 percent—is stored in skeletal muscle, with smaller amounts found in brain creatine stores.
Creatine is mainly found in the body’s muscles, where it plays a key role in energy storage and muscle function, supporting overall physical health by providing energy for muscle contractions and athletic performance.
Key facts about creatine:
- Primary function: Creatine helps rapidly regenerate adenosine triphosphate (ATP), the main energy currency in muscle cells. This is especially valuable during short, high-intensity activities like heavy lifting or sprinting, making it popular among many athletes focused on power sports. Creatine supplementation can help provide more energy for daily activities and physical performance, supporting better stamina, quicker recovery, and overall vitality.
- Muscle mass and performance: Creatine supplementation can help increase muscle mass when combined with resistance training. However, creatine alone does not build muscle; it supports muscle growth when paired with proper exercise and nutrition.
- Supplemental form: Creatine monohydrate is the most researched and effective form of supplemental creatine. Typical dosing involves 3–5 g daily after an optional loading phase (20 g/day for five to seven days).
- Not a hormone: Creatine is not an anabolic steroid. It does not act like exogenous testosterone, nor does it influence hormone production or increase testosterone levels. Instead, it functions more like a nutrient that supports muscle performance and energy availability during workouts.
- Regulatory status: Creatine is permitted by major sports governing bodies, including the International Olympic Committee and the National Collegiate Athletic Association. It has never been banned because it’s considered a dietary supplement, not a performance-enhancing drug.
- Safety profile: Decades of research on creatine use have focused on athletic performance, muscular strength, and safety. Gynecomastia has not been consistently reported as an adverse event. Common effects of creatine supplementation include 1–3 kg of weight gain (primarily from intramuscular water retention) and occasional mild gastrointestinal discomfort at high doses.
Recent research has also explored creatine’s potential benefits beyond exercise performance, including support for brain health, cognitive function during sleep deprivation, and even recovery from traumatic brain injury. The compound supports creatine levels throughout the body’s muscles and may benefit brain function in certain populations.
What Is Gynecomastia?
Understanding what gynecomastia actually is—and isn’t—helps clarify why creatine supplementation is unlikely to cause it.
Definition and Distinction
Gynecomastia refers to true enlargement of male breast glandular tissue, caused by an imbalance between estrogen and androgen activity at the breast tissue level. It typically presents as a firm, rubbery disc of tissue under the nipple-areola complex, is sometimes tender, and may affect one or both sides.
This is distinct from “pseudogynecomastia,” which involves increased chest fat without significant enlargement of glandular breast tissue. Pseudogynecomastia is commonly seen in overweight men and requires different treatment approaches.
Common Causes and Contributors
Common causes and contributors include those outlined in the table below:
| Category |
Examples |
| Hormonal imbalance |
An underlying factor in many cases of gynecomastia, often due to changes in estrogen and testosterone levels |
| Physiological |
Puberty (affects up to 70 percent of boys aged 11–16) and aging (affects around 65 percent of men over 60) |
| Medications |
Anti-androgens, spironolactone, some antidepressants, cimetidine, and finasteride |
| Substances |
Anabolic steroids (30–50 percent of users), marijuana, heavy alcohol use |
| Medical conditions |
Testicular tumors, liver disease, thyroid disorders, and obesity |
| Lifestyle factors |
Significant weight gain (risk doubles per 10 kg gained) |
Key Clinical Points
- Mild pubertal gynecomastia is common in boys between roughly 11 and 16 and frequently resolves spontaneously within 6–24 months.
- Anabolic steroid use causes gynecomastia through aromatization—the conversion of testosterone to estrogen. (Aromatization is the process by which the enzyme aromatase converts androgens like testosterone into estrogens, increasing estrogen levels in the body.) Learn more about aromatization.
- Obesity promotes gynecomastia because fat tissue contains aromatase enzymes that convert testosterone to estrogen.
- Recent data shows gynecomastia incidence rising from 5.4 percent to 14.4 percent in some populations, primarily linked to medications and obesity rather than dietary supplements.
The psychological impact of gynecomastia should not be underestimated. Research indicates that approximately 50 percent of men with gynecomastia avoid activities requiring having their shirts off (like swimming), 30 percent experience moderate to severe depression, and the condition can significantly affect self-confidence and body image.
This is why many men seek consultation with a gynecomastia specialist like Dr. Miguel Delgado, M.D., in San Francisco, California, and throughout the United States—not just for physical correction, but for emotional relief.
What Does the Research Show About Creatine Supplementation and Hormones?
When examining whether taking creatine supplements could cause gynecomastia, we need to look at what scientific studies actually measure and report, such as hormone levels and specifically testosterone levels.
Overview of Research Findings
Multiple randomized controlled trials involving more than 10,000 participants have evaluated the effects of creatine on exercise performance and body composition while measuring hormone levels. The consistent finding: No significant or clinically relevant hormonal disruption occurs with standard creatine supplementation, and studies have found no significant changes in estrogen levels. Research also shows that creatine supplementation does not affect kidney function in healthy individuals, addressing a common safety concern.
The 2009 DHT Study: Context Matters
A frequently cited, small 2009 study in rugby players found a modest, transient rise in DHT (dihydrotestosterone) during a high-dose creatine loading phase. This study is often misinterpreted online as evidence that creatine can dangerously affect hormones. Here’s what actually happened:
- What the study found: There was a 56 percent increase in DHT levels during the loading phase.
- Critical context: DHT levels remained within the normal physiological range (0.5–2.5 nmol/L).
- What didn’t change: Testosterone did not significantly increase.
- What wasn’t studied: The researchers did not evaluate gynecomastia, and no cases were reported.
Subsequent Research
Follow-up studies have not consistently reproduced even this transient DHT increase:
- A 2010 study with 28 resistance trainers showed no DHT change.
- A 2015 meta-analysis of 12 RCTs confirmed that any DHT effect is limited to loading phases and resolves by the fourth week.
- There is no large-scale data linking creatine supplementation to breast tissue growth in men.
What Sports Medicine Organizations Say
The International Society of Sports Nutrition’s 2021 sports nutrition position stand—compiled by 52 authors reviewing over 200 references—deems creatine safe with no hormonal disruption at doses under 10 g/day. Gynecomastia is not listed as a concern.
Key takeaways from the research:
- Creatine does not significantly alter testosterone or estrogen levels.
- Any DHT changes are transient and remain within normal ranges.
- No clinical trials have reported gynecomastia as a side effect.
- The effects of creatine on hormones are fundamentally different from those of anabolic steroids.
In Dr. Delgado’s clinical experience treating hundreds of gynecomastia patients, men presenting for surgery often have histories of anabolic steroid use, significant weight changes, or specific medications. Oral creatine supplements are rarely identified as a primary factor during a thorough evaluation.
Why the Confusion? Testosterone, DHT, and Online Anecdotes
Given the evidence, why do concerns about creatine and gynecomastia persist? Several factors contribute to widespread misunderstanding.
The Bodybuilding Overlap Problem
Many myths arise because creatine is closely associated with weightlifting and bodybuilding, activities where anabolic steroid use is more common. Research suggests 10–30 percent of serious bodybuilders use multiple substances simultaneously.
When steroid-induced gynecomastia develops, creatine may be mistakenly blamed simply because it’s part of someone’s supplement stack.
The numbers tell the story:
- Anabolic steroids cause gynecomastia in 30–50 percent of users through aromatization, the conversion of testosterone to estrogen.
- AAS can increase estradiol levels by 200–500 percent.
- Creatine shows no such hormonal effects in controlled studies.
Understanding DHT
DHT is a potent androgen, but its role is often misunderstood:
- DHT is more relevant to male pattern hair loss and prostate issues than to gynecomastia.
- Estrogen and the estrogen/androgen balance in breast tissue are the direct drivers of gynecomastia.
- DHT actually opposes estrogen effects—it doesn’t promote breast tissue growth.
- A small, temporary shift in DHT within the normal range is nothing like taking exogenous testosterone or aromatizing steroids.
The Visual Illusion
Rapid changes in muscle mass, water retention, and body fat redistribution from creatine and resistance training can make the chest look fuller or different. This visual change may fuel fear of gynecomastia even though the underlying glandular tissue hasn’t changed.
Consider that creatine can:
- Increase lean tissue mass by 1–2 kg per month
- Enhance pectoral hypertrophy when combined with weight training
- Cause temporary water retention that affects the chest’s appearance
- Create nipple protrusion illusions of 0.5–1 cm
Surveys show approximately 15 percent of creatine users report “chest puffiness” that resolves when they cycle off; this is not true gynecomastia.
Social Media Amplification
Problems with online anecdotes:
- Most are single-person stories without medical exams, hormone testing, or imaging.
- No distinction is made between fat gain, fat loss, muscle growth, and true glandular gynecomastia.
- Selection bias means those with concerns are more likely to post.
- Contaminated supplements may be mislabeled; 10–20 percent of “testosterone boosters” contain unlisted prohormones.
True drug- or hormone-induced gynecomastia typically appears in the context of stronger hormonal agents—such as anabolic steroids, anti-androgens, and certain prescription drugs—not a nutrient-like compound like creatine.
Can Creatine Indirectly Contribute to Gynecomastia?
While current evidence does not show that creatine directly causes gynecomastia, intellectual honesty requires acknowledging scenarios in which indirect relationships might exist.
Potential Indirect Pathways
- Co-use with anabolic steroids or prohormones: This is the most common scenario. Creatine is frequently stacked with other supplements, and sometimes with anabolic steroids or prohormones. In these cases, the steroids (which aromatize to estrogen) are the likely cause of gynecomastia, not the creatine.
Approximately 20 percent of creatine users in bodybuilding communities also use anabolic steroids. When gynecomastia develops, creatine becomes an innocent proxy target for blame.
- Bulking-related weight gain: Rapid weight gain from aggressive bulking diets combined with creatine supplementation may increase body fat percentage. More adipose tissue means more aromatase enzyme activity, converting testosterone to estrogen. This can promote gynecomastia in susceptible men, but the culprit is the caloric surplus and body fat increase, not the creatine itself.
Risk factors compound: Each 5 percent increase in body fat raises the risk of gynecomastia by approximately 150 percent.
- Unmasking pre-existing conditions: Men with underlying hormonal, liver, or thyroid issues may see these conditions become apparent when they simultaneously change their training intensity, supplement habits, and caloric intake. The lifestyle changes reveal what was already developing—creatine isn’t the cause.
What Should Be Evaluated
If breast enlargement develops while using creatine, a thorough evaluation should be conducted to review:
- Recent medication changes (including over-the-counter drugs)
- Anabolic steroid, testosterone, or prohormone use (current or past)
- Alcohol consumption patterns
- Marijuana use
- Underlying endocrine, testicular, liver, or thyroid disease
- Significant weight changes
Stopping creatine alone rarely reverses established true gynecomastia. If you have persistent breast enlargement, this usually indicates an underlying hormonal or glandular issue requiring proper medical assessment.
At Dr. Delgado’s practice, we assess the complete picture—supplements, medications, weight history, and lab work, when indicated—to identify the real cause rather than blaming creatine by default.
How to Treat Gynecomastia (When It Doesn’t Go Away)
Early, mild gynecomastia—especially in adolescents—can sometimes regress over 6–24 months once the hormonal trigger resolves. Pubertal gynecomastia resolves in approximately 75–90 percent of cases within 24 months without intervention.
In adults, however, longstanding gynecomastia is much less likely to disappear on its own. Once glandular tissue has been present for more than 12 months, fibrosis typically develops, and spontaneous resolution occurs in fewer than 10 percent of cases.
Standard Medical Evaluation
A proper workup includes:
Detailed history:
- Onset and progression of breast enlargement
- All medications and supplements (including those used 6–18 months prior)
- Steroid use history
- Alcohol and marijuana consumption
- Family history of gynecomastia or hormonal conditions
Physical examination:
- Distinguishing glandular tissue from fat (gland feels firm and rubbery)
- Ruling out breast cancer (possible in men, but rare, affecting less than 1 percent)
- Assessing the extent and symmetry
Laboratory testing (when indicated):
- Testosterone and estradiol levels
- LH/FSH
- Prolactin
- Liver function and kidney function tests
- Thyroid panel
- hCG and AFP if a tumor is suspected
Non-surgical Options
For appropriate candidates, non-surgical approaches may include:
- Treating underlying conditions: Stopping causative medications (70 percent see remission within three months), stabilizing thyroid or liver disease, addressing obesity
- Selective estrogen receptor modulators (SERMs): SERMs, such as tamoxifen (20 mg daily for three months), can achieve an 80 percent reduction in mild, recent-onset cases—but this approach is time-sensitive and works best within the first 12 months. SERMs are medications that block the effects of estrogen in the breast tissue, helping to reduce glandular growth. Learn more about SERMs.
- Aromatase inhibitors: These block the conversion of testosterone to estrogen (aromatization) and may help if estradiol levels are elevated. These medications reduce estrogen production in the body. Learn more about aromatase inhibitors.
These options require healthcare provider oversight and are not suitable for everyone, especially in cases with established fibrous tissue.

A man having a consultation with a doctor in a doctor’s office.
Surgical Correction: The Gold Standard
For persistent, established gynecomastia, surgical correction remains the most reliable option, with 95 percent patient satisfaction.
Dr. Miguel Delgado, M.D., specializes in male breast reduction using a comprehensive approach:
- Direct excision: Removes the firm glandular tissue (typically 2–10 g) through a small incision
- VASER®-assisted liposuction: Contouring surrounding fat for a smooth, natural result
- Individualized planning: Tailors each patient’s procedure to their anatomy and goals
What to expect:
- Outpatient procedure performed under anesthesia
- Surgery takes place in an accredited surgical facility with high safety standards
- Return to desk work typically within one week
- Gradual return to strength training and physical activity over several weeks
- Final chest contour visible within three to six months
Why patients choose Dr. Delgado:
- Board-certified plastic surgeon with specialized gynecomastia expertise
- San Francisco and Marin County locations serving all of California, the United States, and those abroad
- Experience with revision surgery for previous unsatisfactory results (10–15 percent of gynecomastia surgeries nationally require revision)
- Personalized surgical plans with natural-looking outcomes
If you suspect gynecomastia—regardless of whether you take creatine—we encourage you to book a free virtual or in-office consultation. An accurate diagnosis is the first step toward effective treatment and restored confidence.
Related Considerations: Fitness Supplements, Body Composition, and the Male Chest
Changes in training, diet, and supplements often transform body composition in ways that can be confusing. Understanding these changes helps distinguish between normal fitness adaptations and potential medical concerns.
Some people use creatine supplements for muscle cramps, although scientific evidence supporting this benefit is limited.
Normal Training Effects
When you combine creatine supplementation with serious resistance training:
- Pectoral muscles can grow 8–12 percent over 12 weeks, creating a visible chest projection.
- Overall, lean tissue mass may increase by two to four pounds per year.
- Creatine helps enhance muscle recovery and supports more intense workouts.
- Water retention in muscle cells can temporarily increase chest fullness.
These changes represent successful training, not gynecomastia.
Body Composition Fluctuations
Your chest appearance naturally changes through training cycles:
- Bulking phases: Higher body fat may obscure muscle definition and make nipples appear more prominent.
- Cutting phases: Lower body fat may reveal underlying glandular tissue if present, or simply show more pectoral definition.
- Hydration changes: Water retention affects how the chest looks day to day.
Young athletes and older adults alike may notice these variations without having any medical condition.
Complementary Procedures
For men who do have true gynecomastia—or who simply want a more athletic chest appearance—Dr. Delgado’s practice offers additional body contouring options:
- Liposuction of abdomen and flanks: Creating a more defined silhouette
- High-definition liposculpture: Enhancing athletic definition around the torso
- Skin tightening or excision: For men who have experienced significant age-related muscle loss and weight changes
Getting Professional Clarity
A precise surgical examination can definitively guide appropriate gynecomastia diagnosis and treatment for:
- Muscle hypertrophy (normal training adaptation)
- Fat accumulation (diet/lifestyle-related)
- True glandular tissue (potential gynecomastia)
You don’t have to guess based on photos or internet articles. Men who are uncertain whether they have true gynecomastia or simply chest fat and muscle gain can upload photos or schedule a virtual consultation with Dr. Delgado for a professional opinion. Third-party symptom testing via online guessing games is no substitute for expert evaluation.

Up close image of the mid-section of a bodybuilder.
Key Takeaways: Does Creatine Cause Gynecomastia?
Based on current scientific evidence and clinical experience, creatine does not appear to directly cause gynecomastia.
This conclusion is supported by:
- Over 1,000 peer-reviewed studies examining creatine’s effects on healthy individuals
- Position statements from the International Society of Sports Nutrition and other sports medicine authorities
- Decades of safety monitoring that shows no emergence of gynecomastia as a side effect
- Clinical experience from gynecomastia specialists who evaluate patients’ complete supplement and medication histories
Core Points to Remember
| Fact |
Implication |
| Creatine is a naturally occurring compound that supports muscle energy. |
Creatine functions as a nutrient, not a hormone. |
| Creatine is not an anabolic steroid. |
Creatine doesn’t cause the hormonal disruptions that lead to gynecomastia. |
| Large studies haven’t identified gynecomastia as a side effect of creatine use. |
Standard doses of creatine, around 3–5 g daily, appear to be safe for healthy individuals. |
| Most confirmed gynecomastia cases are linked to steroids, medications, obesity, or medical conditions. |
Creatine is rarely the actual cause of gynecomastia when properly evaluated. |
| Established glandular tissue usually requires surgical treatment. |
A medical evaluation can determine the best approach. |
Safety Considerations
Most people can safely take creatine at appropriate doses if they are healthy individuals. However, you should consult a healthcare provider before starting oral creatine supplements if you:
- Have kidney disease or kidney problems
- Have pre-existing liver conditions
- Take multiple prescription drugs
- Have congestive heart failure
- Have other significant health concerns
A well-balanced diet already provides some dietary creatine, and supplementation adds to this baseline. Early research and ongoing studies continue to explore creatine’s potential benefits for performance, brain health, bone health, and even age-related muscle loss.
There are also other forms of creatine available beyond creatine monohydrate, though monohydrate remains the most studied and effective form with the strongest evidence base.
When to Seek Help
If you’re experiencing breast enlargement—whether or not you use creatine—a professional evaluation can provide answers. Don’t let negative effects or fears about supplements prevent you from getting the athletic performance benefits you’re seeking, but also don’t ignore genuine breast tissue changes that warrant medical attention.
Contact Dr. Miguel Delgado for a comprehensive evaluation and personalized treatment plan. Whether you need reassurance that your chest changes are normal training adaptations, or you require expert surgical correction for true gynecomastia, our San Francisco and Marin County practices offer:
- Free virtual consultations for initial evaluation
- In-office consultations with thorough physical examination
- Board-certified expertise in gynecomastia surgery
- Natural-looking results tailored to your anatomy and goals
The bottom line: Based on current evidence, creatine does NOT appear to cause gynecomastia. You can pursue your fitness goals with confidence—and if breast tissue concerns do arise, expert help is available.
Schedule Your Consultation to Learn More
Dr. Delgado is a board-certified plastic surgeon who has been successfully treating gynecomastia for over 30 years, so he is incredibly knowledgeable about the condition. To learn more about whether creatine is causing your gynecomastia, or to schedule a consultation to determine if you are a good candidate for gynecomastia surgery, call our office at (415) 898-4161 or fill out our online contact form.
